

 Çerez Tercihleri
Tarama deneyiminizi geliştirmek, kişiselleştirilmiş içerik sunmak ve trafiğimizi analiz etmek için çerezler kullanıyoruz. Lütfen aşağıdan tercihlerinizi seçin.
Hairline Shape & Temporal Design
- Hair Transplantation Is More Than a Graft Number
- Understanding Hair Transplantation
- Hairline Shape & Temporal Design
Hairline Shape & Temporal Design
More Than a Line Across the Forehead
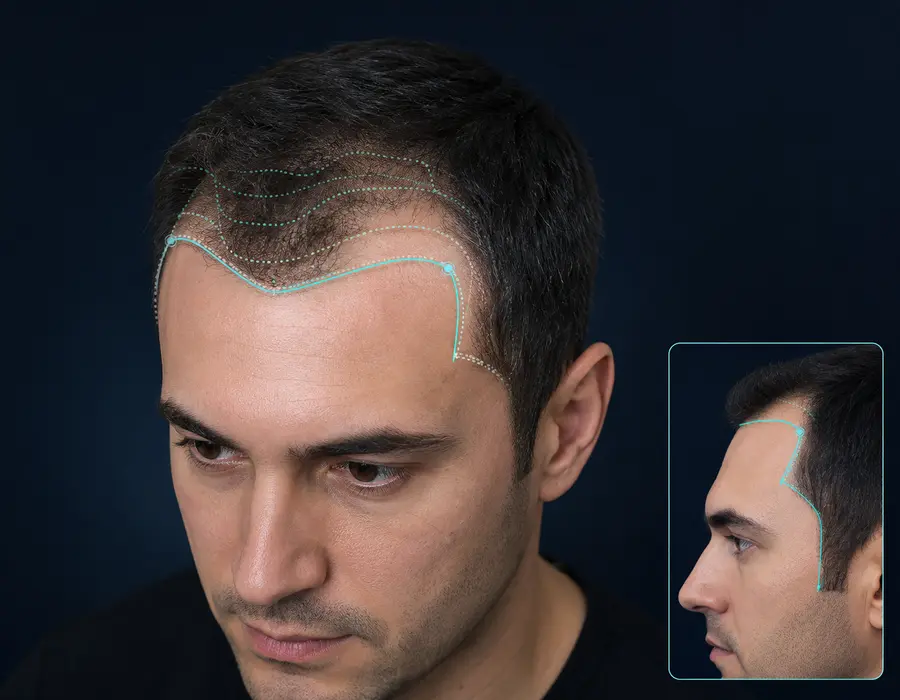
Hairline design is not limited to drawing a boundary between the forehead and the scalp. The central frontal area, frontal corners, temple recessions, temporal hairline and side hair form a connected frame around the face.
A proposal that appears acceptable from the front may look disconnected when viewed from the side. For this reason, hairline shape and temporal design should be reviewed together and from several viewing angles.
The aim is not to select a fashionable outline. It is to develop a contour that relates to the individual’s anatomy and remains compatible with the broader treatment plan.
Shape and Position Are Different Decisions
Hairline position describes where the frontal boundary begins. Hairline shape describes how that boundary travels across the forehead and connects with the temples.
A suitable position does not automatically create an appropriate shape. The contour may be influenced by:
Forehead width and curvature
Central facial axis
Existing frontal hair
Frontal and temporal recession
Skull shape
Temple anatomy
Age and expected progression of hair loss
Hair calibre, curl and direction
Available donor capacity
Recipient-area size
These variables should be considered together rather than applying one standard outline after selecting the central point.
Fixed Shape Labels Have Limitations
Hairlines are sometimes described as rounded, U-shaped, V-shaped, straight or M-shaped. These labels may help explain broad concepts, but they should not be treated as ready-made designs.
Many natural hairlines combine several characteristics. The central contour may be gently curved while the frontal corners remain slightly recessed. One side may also differ subtly from the other because facial and skull anatomy are not perfectly symmetrical.
Selecting a shape from a catalogue cannot replace individual assessment.
The Central Frontal Area
The central frontal region is often the most visually prominent part of the design. Its width, curvature and relationship with the forehead influence how the face is framed.
An excessively flat central contour may appear rigid. An exaggerated central projection may also look disconnected from the frontal corners.
The proposed shape should be evaluated in relation to the person’s existing anatomy and should not be designed independently from the areas immediately behind it.
Frontal Corners
The frontal corners connect the central hairline with the temporal recessions. Their height, width and curvature can substantially change the overall appearance of the design.
Closing the corners aggressively may:
Increase the recipient surface area
Require additional grafts
Reduce visible temporal recession
Alter the side profile
Limit resources available for future thinning
Become difficult to maintain if surrounding native hair recedes
Leaving some age-appropriate recession may create a more sustainable transition. The appropriate degree cannot be determined by age alone and requires individualized assessment.
Understanding the Temporal Area
The temporal region includes the upper outer corners where the forehead meets the hairline. The temporal point is the lower triangular projection where the temporal hairline approaches the sideburn.
These structures influence the apparent width of the forehead and the balance between the front and side of the face.
Temporal recession is also commonly involved in progressive patterned hair loss. Reconstruction should therefore be considered cautiously and within the long-term plan.
Temporal Points Are Specialized Structures
Temporal points are not simply small extensions of the frontal hairline. Their hair may differ from central scalp hair in:
Calibre
Density
Direction
Angle of emergence
Length
Relationship with the sideburn
The hairs commonly lie at acute angles and follow changing directions. A poorly integrated temporal point may appear isolated or artificial even if the frontal line itself is acceptable.
Temporal-point planning is therefore a specialized decision rather than an automatic component of every hairline procedure.
Temple Closure Is Not Always Necessary
Not every patient requires reconstruction of the temples or temporal points.
The decision may depend on:
Existing temporal hair
Degree and stability of recession
Facial width and shape
Hairstyle
Hair calibre and donor characteristics
Available graft numbers
Expected future hair loss
Patient priorities
The visual effect from the side
In some patients, preserving a degree of temporal recession may be more coherent than attempting complete closure.
Direction and Angle Affect the Design
A line drawn on the skin does not fully describe how the hair may appear. Hair direction and angle influence whether the frontal and temporal regions seem connected.
Central frontal hair may have a predominantly forward direction, while the direction changes progressively toward the frontal corners and temples. Temporal hairs often emerge at more acute angles and follow the contour of the side of the head.
Recipient-site creation and graft orientation are medical and surgical stages. They require an understanding of regional anatomy and should not be treated as mechanical placement tasks.
Existing Hair Should Be Examined
Remaining hairs within the frontal corners and temporal regions may provide useful information about previous anatomy and growth direction. However, they may also show miniaturization and may not remain stable.
Planning should distinguish between:
Stable existing hair
Miniaturized hair
Isolated remnants of the former hairline
Previously transplanted grafts
Areas likely to recede further
A design that depends entirely on unstable native hair may become disconnected if that hair later thins.
Natural Asymmetry
Natural faces, foreheads, temples and hairlines are rarely perfect mirror images. One frontal corner may be higher, one eyebrow may sit differently or the skull contour may vary between sides.
The design should recognize these differences. Exact symmetry imposed on an asymmetric face can appear less natural than a controlled degree of variation.
This does not mean that every existing asymmetry must be reproduced. It means that any adjustment should be deliberate and explained rather than hidden within a standard template.
Shape Influences Graft Requirements
Changing the frontal contour or closing the temples increases or reduces the surface area requiring coverage.
A small change on the drawing may therefore have meaningful consequences for:
Total graft demand
Distribution between the frontal and central scalp
Density priorities
Donor preservation
Future treatment options
The proposed shape should be considered together with graft availability. A visually ambitious outline that cannot be supported by the donor plan may create weak coverage or consume resources needed later.
Hair Characteristics Influence Visual Balance
The same outline may produce a different visual effect depending on:
Hair-shaft calibre
Curl or wave
Hair and skin colour contrast
Follicular-unit composition
Existing recipient hair
Styling direction
Coarse or curly hair may provide visual coverage differently from fine, straight hair. These characteristics should influence the overall plan, but they do not establish a guaranteed density or outcome.
Review from Multiple Angles
A proposed design should be evaluated from:
Directly in front
Both three-quarter views
Both side views
Above
The patient’s usual viewing and styling position
The side view is particularly important for assessing the relationship between the frontal corner, temporal hairline, temporal point and sideburn.
Standardized photographs may help document these relationships and the alternatives discussed.
Digital Designs Are Explanatory Tools
Digital drawings, overlays and simulations may help compare possible contours. They cannot accurately predict final growth, density, texture or biological response.
A digital image may also hide irregularities or create unrealistic expectations if interpreted as a promised result.
The final design should be confirmed during direct assessment and documented before the procedure.
Questions Worth Asking
Before accepting a proposed shape, patients may wish to ask:
How does the contour relate to my facial and skull anatomy?
Was it reviewed from the front and side?
Why were the frontal corners left open or closed?
Are the temples or temporal points included?
How would temporal reconstruction affect graft requirements?
Does existing hair in these areas show miniaturization?
How could future recession change the appearance?
How will hair direction vary between the front and temples?
Is natural facial asymmetry being considered?
Is the proposal compatible with long-term donor capacity?
Who is responsible for the design and recipient-site planning?
Will the final agreed outline be documented?
The answers should explain the individual reasoning behind the proposal rather than referring only to a named shape or standard template.
The Central Principle
Hairline shape and temporal design should form a continuous, individualized frame around the face.
A balanced proposal integrates frontal contour, corners, temples, viewing angles, hair direction, progressive hair loss and finite donor resources. It does not depend on perfect symmetry, complete temporal closure or a predefined geometric shape.
The final design requires direct medical assessment. General diagrams, photographs and website information cannot determine the appropriate contour for an individual.
Educational References
International Society of Hair Restoration Surgery — Hair Restoration Surgery Glossary
International Society of Hair Restoration Surgery — The Recipient Site: Where the Science and Art of Hair Transplant Are Applied
International Society of Hair Restoration Surgery — Hairline Design Webinar
International Society of Hair Restoration Surgery — Using Your Hair to Create Your Uniquely Individual Hair Restoration
External sources are provided for general educational reference. No affiliation or endorsement is implied.
This content is intended for general educational purposes and does not replace an individualized medical examination, diagnosis or treatment plan.
Diğer Hizmetler

Understanding Scarred Scalp Tissue
Scarred scalp tissue may

Facial Proportions & Hairline Position
Hairline position should
What Matters in Hair Transplantation
Hair transplantation shou

Medical Assessment & Candidacy
Suitability for hair tran

Positioning During Prolonged Procedures
Hair transplantation may

The Role of the Nurse in Telehealth-Based Hair Transplant Follow-Up
Nurse-led telehealth foll

Master’s Thesis Research: Wound Healing and Infection Prevention in Hair Transplantation
This page introduces a pu

Assessing Donor Capacity
Donor capacity cannot be

Balanced Extraction & Homogeneous Distribution
Donor preservation depend
Hairline Shape & Temporal Design
Hairline shape should con

Suitability, Donor Capacity and Staged Planning
Suitability for hair tran

Non-Pharmacological Comfort Support
Comfort during a prolonge

Burn Alopecia: Nursing Care and Psychosocial Support
Burn-related alopecia may

Donor Area Preservation
The donor area is a limit

Understanding FUE and DHI
FUE describes how follicu

Individualized Planning & Natural Hairline Design
Hairline design should be

Graft Numbers, Density & Distribution
A graft count alone does

Natural Irregularity & the Transition Zone
A natural-looking hairlin

Healing, Follow-Up and Realistic Expectations
Healing in scarred scalp

When Beard Donor May Be Considered
Beard hair may be conside

Complications, Patient Safety and Forensic Evaluation
Patient safety in hair tr

Direction, Angle & Density Transitions
Hair does not emerge from
Patient Comfort & Physiotherapy Support
Hair transplantation may

Who Performs Each Stage?
Hair transplantation invo
Aftercare & Structured Follow-Up
The period after hair tra

Planning for Women & Different Hair-Loss Patterns
Hair loss in women may pr

Risks, Limitations & Realistic Expectations
Hair transplantation is a
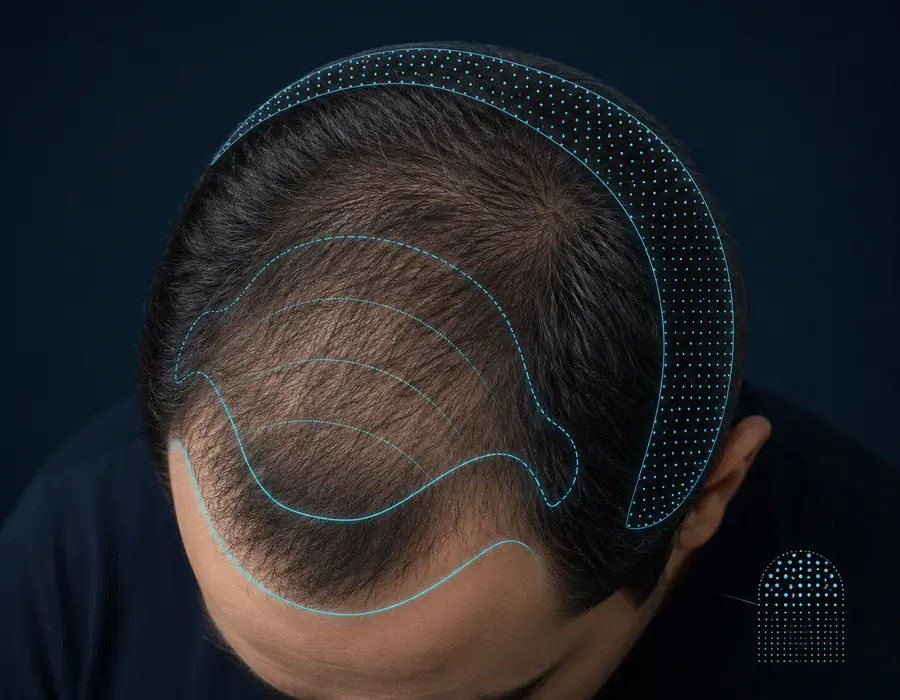
Long-Term Planning & Future Hair Loss
Pattern hair loss may con

Academic Research & Clinical Insights
Easesthetic’s academic fo
Hair Transplantation in Scarred Tissue
Hair transplantation in s
Frequently Asked Questions